
Avastin (bevacizumab), Provenge (sipuleucel-T) Two More Reasons Why Health Care is Bankrupting Us

The drugs Avastin (bevacizumab) and Provenge (sipuleucel-T) are two of the most expensive drugs in the world. Bevacizumab costs in the range of $100,000/year for treatment and simuleucel $93,000 for a course of treatment.

Neither cures patients. In studies in breast cancer bevacizumab has been found minimally effective, if at all. When compared to outcomes of patients not using the drug, It appears to delay progression by a few months and survival by even less then that (between no survival advantage to a few months). Sipuleucel-t gives about the same degree of response in prostate cancer. Despite this apparent lack of efficacy, and the advice of an FDA advisory board, Medicare has decided to continue to pay for the use of these agents.

The problems with these drugs are two-fold. One, they do very little to improve survival. And second, they are outrageously priced.

Regarding pricing, we’ve allowed drug companies to price drug grotesquely by:

  • Providing them government sponsored monopoly (a patent) for a generation. (so much for free markets)
  • Allowing drug companies to take drugs developed in part with government research funding private without offsetting the government’s investment by requiring licensing or reasonable pricing of the drug
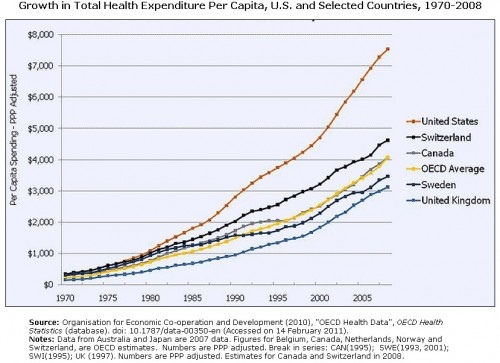
  • Prohibiting Medicare from negotiating price with drug companies. This was part of the Medicare D law and has resulted in the inexorable upward spiraling of drug prices. We pay more for drugs in the U.S. than anywhere else in the world. WE ARE NUMBER 1!
  • Cost effectiveness is not in our health care system’s vocabulary. We regularly use drugs with limited to no effectiveness.

Medicynical Note: For many years as an oncologist I used drugs with limited efficacy just on the chance that my patient might benefit. Desperate people accepted remarkable levels of toxicity in the hope that they will be the lucky ones and have a long survival benefit. During treatment, they all thought the drug was working, until it became clear that the disease was progressing. In retrospect very little of the “response” (and I’m thinking of patients with colon cancer treated with 5FU during the 70’s and 80’s) was tumor regression due to the drug. We almost never saw tumor’s decrease in size. Rather each cancer has a biology that affects how rapidly it will grow and recur. There are other poorly understood factors such as the patient’s immune system’s affect on tumor growth that also may come into play. But what was clear from comparison studies of 5 FU and no treatment was that very few patients benefitted. It should be noted that at the time 5FU in 500 mg vials cost $5.00.

Medicare has now announced that despite the proven limited efficacy of these drugs (bevacizumab and sipuleucel-T they will continue to pay for them–at the price demanded by the manufacturer.

If we are unable to rationally use these grotesquely expensive agents we will undoubtedly be rationing through increased co-pays, increased cost of insurance, and lo ball insurance that does’t cover such agents.
Drug Costs and Prostate Cancer: Charging a Premium for Minimal Efficacy

The Times has an article highlighting the costs of new drugs for prostate cancer. Mind you, these are drugs that have a very limited ability to extend life in patients with advanced disease.

In the last 15 months, three new drugs that extended the lives of prostate cancer patients in clinical trials have been approved by the Food and Drug Administration and several other promising medicines are in clinical trials.

And:

Men with that late-stage cancer had a median survival of about a year and a half using docetaxel. The new drugs each added two to five months to median survival when tested in clinical trials. Doctors say that men taking more than one of the drugs in succession would be expected to live more than two years. (Medicynical note: The last sentence is completely unproven and highly doubtful if it means to live 2 years beyond the original 18 months achieved by docetaxel alone. One wonders which doctors are saying this?)

And:

Provenge costs $93,000 for a course of treatment, while Zytiga costs about $5,000 a month. Another of the new drugs, Sanofi’s Jevtana, costs about $8,000 every three weeks.

With other pricey drugs on the way, said Joel Sendek, an analyst at Lazard, “We could be talking easily $500,000 per patient or more over the course of therapy, which I don’t think the system can afford, especially since 80 percent of the patients are on Medicare.”

Medicynical Note: New drugs are protected by a government sponsored monopoly (patents), allowing a generation of exclusive use to the developer of the advance.

Health care of course is different from computers or other consumer products. There is limited choice about both the timing, source and type of treatments available, particularly in diseases that have fatal consequences.

As such it’s a wonderful set-up for manufacturers. They have exclusive rights to a product that their customers feel they must have. The customer is buffered from the true cost by his/her insurance coverage. The insurer is under huge pressure from the patient to cover everything that they need and simply passes the costs on to policy holders.

Cost efficacy is not a consideration. Patients believe that they will be the one who will benefit and have excellent results. This is the situation even where 1/2 the patients treated get little or no benefit and the treatment at best provides minimal life extension–as in these drugs. It should be re-emphasized that the judgement that these drugs could provide years of survival is completely untested and likely false.


Bevacizumab (Avastin) for Breast Cancer, Expensive and Mediocre

Todays NY Times reports that Genentech will try to pressure the FDA to continue the bevacizumab (Avastin) indication for treatment of breast cancer.

It should be stated up front that the drug can be used for breast cancer without FDA approval. The question is whether medicare and other insurers should should be forced (by virtue of the FDA approving the indication) to cover a wildly expensive ineffective treatment.

The data on this drug’s lack of efficacy is clear. It was originally approved in a study which showed a delay in progression of disease. At the time of approval, little was known whether patients so treated would actually live longer. Genentech wanted accelerated approval and agreed that followup studies would be done to confirm its efficacy, not only in delaying progression but also in improving survival.

The F.D.A. approved the drug for advanced breast cancer in February 2008, after one clinical trial showed that combining Avastin with another drug, paclitaxel, delayed the median time before tumors worsened by 5.5 months, compared with using paclitaxel alone. But the women who got Avastin did not live significantly longer than those who got only paclitaxel, which is also known by the brand name Taxol.

and:

Subsequent trials, in which Avastin was combined with different chemotherapy drugs, showed a much smaller delay in tumor progression, ranging from less than 1 month to 2.9 months. And again there was no improvement in survival for those receiving Avastin.

Yet another trial showing this drug’s huge costs and limited efficacy was reported on at ASCO 2011, we commented on this trial here. The study reported .49 years delay of progression free survival and just .135 years (about 1.5 months) of life extension–a cost of $745,000 for a QALY (quality adjust life year). Hardly evidence of a cost-effective intervention, or for that matter a drug that works.

This controversy is in part due to the erosion of standards in clinical trials. At one time patients were deemed to show a response if the tumor decreased in size by 50%. The gold standard for an effective treatment was an improvement in survival, not a mere delay in progression.

It turns out unfortunately that a delay in progression often means little in regard to survival and in the case of bevacizumab (Avastin) even that delay is open to question as repeated studies show a more limited delayed progression as well the lack of a significant survival benefit.

Medicynical Note: With drugs as expensive and ineffective as this one is in breast cancer, it’s easy to understand why health care costs are out of control.


ASCO 2011: Cost Effectiveness Abstracts Pancreatic Cancer, Chronic Myelogenous Leukemia, Follicular Lymphoma

These are the last of the very few chemotherapy drug cost-effectiveness studies at ASCO 2011. As noted in previous posts, there very few such studies.

1. Cost effectiveness of systemic therapies for Pancreatic Cancer: (abstract 6114) This study is an incremental cost study comparing the costs of gemcytibine(G), gemcytibine + capecitibine (G+C), gemcytibine + erlotinib (G+E), and FOLFIRINOX (FFX 5-FU, leucovorin, irinotecan and oxaliplatin).

The incremental cost-effectiveness ratios of G+C, G+E and FFX when compared to G were $82,982/QALY, $204,952/QALY and $154,323/QALY, respectively.

The cost of treatment in Canadian dollars was $29,5650 for G, $34,100 for G+C, $46,900 for G+E and $66,000 for FFX. Life expectance was .677 years for G, .76 years for G+C, .79 years for G+E and 1.005 years for FFX.

Medicynical Note: The limited benefit and significant toxicity of the additional treatments highlight our lack of an effective intervention for this diagnosis.

2. Comparison of costs of nilotinib and imatinib in chronic myelogenous leukemia (Abstract 6572) This is a drug company sponsored comparative efficacy study and concludes that the nilotinib is a cost effective alternative to imatinib.

Medicynical Note: The drug costs cited in this study appear to be 3/4 to 1/2 that experienced in the U.S. for example $602,605 over 17.3 years= $34,832/year. In the US costs are cited as between $48,000 and $98,000/year.

3. Cost effectiveness of cetuximab bevacizumab and panitumumab in metastatic colorectal cancer in patients with KRAS (wt) tumors: This is another incremental cost effectiveness analysis sponsored by a drug company. It found that cetuximab was more cost effective than the others in addition to FOLFIRI in patients with KRAS tumors.

Medicynical note: Increment cost effective studies do not add the base costs of FOLFIRI to the analysis. It’s uncertain what the total cost per QALY is compared with other regimens but the study does affirm that cetuximab adds close to $50,000 (conversion from £30,000) to the cost of a QALY.

4. Economic impact of rituximab as maintenance therapy in untreated follicular lymphoma: This drug company sponsored study based on a Markov model found that use of rituximab was cost effective. The cost of a QALY was between $17,000 and $35,000 depending on the relative risk reduction in time to progression.

Medicynical note: I don’t trust drug company studies that do not actually measure costs or outcomes. Using a “model” affords too much room to fiddle with results. Most follicular lymphoma patient do well with watchful waiting rather than immediate therapy. It’s doubtful, in my view, that this is a cost effective intervention.

See here for more discussion of the concept and the fact that other studies of maintenance rituximab show no survival benefit.

However, there was no significant difference in overall survival among the 3 groups, and 96% of the patients are still alive in each group. Whether overall survival will be improved “is currently unclear,”


Health Care: A Moral Value, A Necessity, An Ethical Dilemma

Fine editorial by a bioethicist James Drane: 

Those opposed to any change in the present U.S. health-care system claim that it is already the best in the world, therefore why change it. In fact, an assessment of all health-care systems by the World Health Organization ranks the U.S. system at 37th in the world, right ahead of Slovenia. Five different performance standards were used to measure health systems.

And:

Although the term public welfare is not used in public discussion of health-care here in the U.S., it does belong, and it is not socialism. Public welfare, in fact, is a term found in the first sentence of the Preamble of the U.S. Constitution, ratified in 1788. “We the people of the United States, in order to form a more perfect union, establish justice, insure domestic tranquillity, provide for the common defense, promote the general welfare, and secure the blessings of liberty to ourselves and our posterity, do ordain and establish this Constitution for the United States of America.” One purpose of government, stated in the Constitution, is to promote the general welfare. It refers to the goods that all people need to be free and to enjoy prosperity.

And concludes:

In democracies, citizens are responsible for choosing the moral values of their societies. Voters create good societies through good laws and humane policies. When a large percentage of the population lives in abject poverty, when children die unnecessarily, when elderly persons suffer in isolation, when 46 million people have no health care, the common good is not being achieved and the general welfare is not being provided.

Medicynical Note:  Our democracy’ s approach to health care has it’s grotesque aspects;

  • Political parties (and politicians) selling themselves to highest bidder, an action sanctioned by the Supreme Court
  • Sanctioning “free” ER use as an alternative to a health care access for all citizens
  • Actually, over 50 million are uninsured (and rapidly rising)
  • Health Insurers who don’t want to insure those needing health care
  • Pharmaceutical suppliers gouging the sickest and most helpless in our culture

And so on. 

Our health care non-system is already viewed with incredulity in other industrialized nations.  They are amazed that the “leading nation of the world” would tolerate such an abomination.

To Obama’s great credit he’s taken the first faltering steps in leading towards a more rational humane universal health care system.  The question is whether we’ll evolve further into an efficient coherent economical system or de-evolve into a health disaster and a dead end.

ASCO 2011: Cost effectiveness Zoledronic Acid (Zometa) vs Denosumab (Prolia, Xgeva)

There were very few cost efficacy studies at the recent ASCO meetings.

One set of three studies sponsored by the drug company (Novartis) compared zoledronic acid with denosumab made by Amgen. The abstracts looked at the cost of a QALY (quality adjusted life year) in patients with metastatic prostate cancer (abstract 1), and breast cancer (abstract 2). The third was an economic evaluation (abstract 3) comparing the costs of preventing a skeletal related event in prostate cancer. Not surprisingly, since they were sponsored by Novartis, these studies “confirmed” that zoledronic acid was more “cost effective.”

The studies found that while zoledronic acid is slightly less effective than denosumab in preventing skeletal related events, denosumab is more expensive.

From abstract 1:

Compared to ZOL (Table), Dmab resulted in fewer SREs, more QALYs, and lower SRE-related costs, but higher drug-related and total costs ($5,313). Overall, Dmab resulted in an incremental cost of $1,250,000 per QALY gained.

From abstract 2:

Dmab resulted in fewer SREs, more QALYs, and lower SRE-related costs, but higher drug-related and total costs vs. ZOL, resulting in an incremental cost of $6,884/pt (Table). The cost per QALY gained was $644,000 when excluding SAEs ($613,000/QALY when including SAEs).

It is telling, and perhaps reflects a “strategic” omission, that neither abstract 1 or 2 reveals zoledronic acid’s cost of a QALY gained.

However, abstract 3 gives a better indication of the relative costs and efficacy of the approaches.

The total costs incurred over one year were estimated at $37,854 for denosumab and $30,499 for ZA, with an incrementally higher cost of $7,355 for denosumab. The estimated number of SREs during the one-year period was 0.56 for denosumab and 0.67 for ZA, where the denosumab patients had 0.11 fewer SREs.

QALY= quality adjusted life year
SRE= Skeletal related event

Medicynical Note: What is unstated in these cost comparison studies is that none of the current generation of treatments to prevent bone events including zoledronic acid and the newer monoclonal, denosumab, meet the guideline for cost effectiveness. (a QALY at a cost of less than $50,000-$100,000.

A study in the Journal Urology in 2004 compared the outcomes of patients getting zoledronic acid with patients receiving placebo and noted:

The nominal cost per skeletal complication avoided was US dollars 112300 (95% CI US dollars 6900 to US dollars 48700) and the cost per additional patient free of skeletal complications was US dollars 51400 (95% CI US dollars 26900 to US dollars 243700). Nominal within-trial cost per quality adjusted life-year was US dollars 159200, which varied widely in sensitivity analyses.

To put it in perspective, in 2004 when drug costs were much lower than now, the health care non-system in the U.S. spent over $50,000 to save one additional skeletal complication. That approximates the yearly median income in our country.


Bevacizumab (Avastin) in Breast Cancer — Neither Effective nor Cost-Effective

It’s been well documented that bevacizumab is not very effective in breast cancer.

However, Roche/Genentech continues to lobby it’s use for this indication. At the ASCO 2011 meeting there was yet another study documenting the lack of efficacy and value of the drug in breast cancer. Needless to say there were no company hyped headlines touting the results.

The study from Singapore found:

Bevacizumab added 0.49 years of PFS and 0.135 QALY with an incremental cost of $100,300 and therefore a cost of $204,000 per year of PFS gained and an ICER of $745,000 per QALY.

PFS= progression free survival
QALY= quality adjusted life year
ICER= the additional cost per one life year gained of one treatment over another

Medicynical note: Three reasons why bevacizumab should not be used in breast cancer. High costs, lack of benefits and additional toxicity.

The numbers are embarrassing. $745,000 for an additional life year (ICER). A statistical gain of just .135 life years (QALY).

If Genentech/Roche were to price the drug at 1/10 the current price it would be marginally cost effective, while remaining ineffective in extending life. It’s amazing that there is still a discussion about this indication.


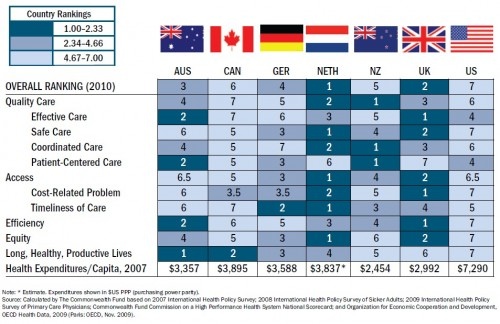
Health Care: We’re Number 7 OVERALL, Number 1 in COSTS


Medicynical Note: At least we’re number 1 in something.


ASCO (American Society of Clinical Oncology) Meetings 2011, Oncology Costs? Value? Cost Effectiveness? Not our Department

The 2011 ASCO meeting ended last week. An estimated 20,000 physicians and others with research and clinical interests in cancer care attended. 4500 abstracts of scientific work were presented with tremendous publicity given to many of the studies, particularly those sponsored by pharmaceutical companies. Reporting on the “event” was obvious on financial pages, daily newspapers and the web.

Drugs and studies touted included the use of exemestane in breast cancer presentation, the use of vemurafenib in melanoma, use of pemetrexed maintenance, bevacizumab in ovarian cancer, targeted therapy, and so on. What was pointedly missing was any emphasis on costs or even mention of the relative cost effectiveness of the various regimens so vigorously publicized.

ASCO accepts a great deal of money from the pharmaceutical industry but even so, as a professional organization in a time when health care spending is soaring, one would think they would pay more than lip service to the problem.

ASCO’s lip service:

In the U.S. health care system, the challenge of coping with cancer, and the effect of both disease and treatment, can be compounded by the uncertainty of whether patients will have access to appropriate care and who will pay for it. It is clear that the costs of cancer care are going up, driven in large part by innovation and by our ability to do more for patients.

In many settings these costs are being shifted to our patients, with a poorly understood effect on access to care and treatment decisions. There is a clear need to better understand the financial effect of cancer care on our patients and how we as oncologists can best promote informed decision making and access to appropriate care.

And:

For decades, it has been clear that a lack of health insurance leads to patients with cancer presenting with more advanced stages of disease at the time of diagnosis and to worse outcomes. The recent passage of the 2010 Patient Protection and Affordable Care Act promises to reduce the ranks of the uninsured, currently estimated at more than 50 million people.

More than 25 million additional Americans may be considered “underinsured” based on inadequate coverage for medical expenses. Ideology aside, we likely can agree that all patients with cancer should have access to quality health care, and that guaranteed access to screening, timely diagnosis, treatment, and supportive care should be our priority for any emerging policy. At this time, there is a patchwork of services and support that can provide financial assistance for patients with cancer.

And:

Despite the availability of financial assistance programs, one-third of patients with cancer report trouble paying their bills and up to 25% report exhausting their savings. These figures are perhaps not surprising in light of the costs of treatment, particularly with novel molecularly targeted agents. Drugs that extend median survival by several months may be priced at as much as $100,000 per patient.

Costs are indeed a problem in our chaotic non-system of care. Where else in the industrialized world do you find 50 million uninsured and people bankrupted by health care costs. Only in America.

When searching the 4500 abstracts of presentations at ASCO 2011 for the word “cost” 286 (6.3% ) studies were found. On review most of these abstracts mention the word “cost” but do no analysis of the actual cost of the intervention.

When the 4500 abstracts were searched for the words “cost effectiveness” a mere 50 (1.1%) studies are highlighted. Once again the great majority of these don’t measure cost effectiveness. In the end fewer than 15 or less than .3% of all presentations were cost effectiveness analyses.

Part of the problem of course is funding. Drug companies are not interested in cost containment, cost efficiency, or value. Rather, their primary goal is ever increasing revenue and profits. They rarely fund cost effectiveness or comparative effectiveness studies unless they are trying to gain an edge over a competitor’s product. And if the study doesn’t show the company’s product positively, they are not publicized, presented or published.

Over the next couple of weeks I’ll review some of the studies of cost effectiveness and point out a few that PHarma did not tout during its publicity blitz last week.

If you are interested you can browse the 2011 abstracts yourself.


Reality in Iowa? Crossing the Border for Health Care

Interesting editorial in the Des Moines Registeron traveling for care:

It simply isn’t true. The United States does not lead the pack on health care.

Not according to the World Health Organization, which ranks health care systems of countries all over the world.

Not according to the millions of uninsured Americans who likely think Canadians waiting for elective knee or hip replacements have it pretty good. Most Americans who are uninsured cannot be examined by a family practice doctor or receive mental health treatment or surgery or medications because they cannot afford to pay for them. That is the definition of rationing medical services in a country that spends more on health care than any country on the planet. (Medicynical emphasis)

and:

The most obvious example are the thousands who fill prescriptions at pharmacies in other countries. They may drive across the border or use an Internet pharmacy.

and:

According to one study, 750,000 Americans traveled abroad for health care in 2007 — almost double the number of nonresidents who came to the United States for treatment. Americans, particularly younger ones, head oversees for such services as stem-cell treatments, cosmetic surgery, or tubal ligations. They go elsewhere because it is cheaper.

Medicynical Note: America’s self-delusion does show signs of ending.