Women and Children pay first: Cuts to WIC program pay for Tax Cut to the Wealthiest

This apparently is the new American way. The proposed cuts are based on bogus analysis:

In deriving the 40 percent figure, the Committee apparently misunderstood a finding in a federal Agriculture Department (USDA) report that for every $1 in federal WIC funds spent for WIC foods in 2006, another

  • 41 cents in federal funds went for administrative costs plus WIC nutrition services. But: 41 cents out of $1.41 in expenditures equals 29 percent, not 41 percent; and
  • over two-thirds of that 29 percent goes not for administrative costs but instead for core WIC services such as breastfeeding support, nutrition education, smoking cessation support, diet and health assessments, substance abuse screening and education, and referrals for immunizations and other needed care.

Medicynical Note: Strange but true. The sad state of the U.S. economy allows such travesties. We’ve sold our soul to the……..banks, corporations and such.


Improving Health Care: Women’s life expectancy falls

For years our, the U.S. non-healthcare system’s emphasis has been on treatment. We go to extremes at great cost and have little benefit in terms of survival of our population. For example, women, “in large swaths of the U.S. are dying younger than they were a generation ago”.

But over the last decade, the nation has experienced a widening gap between the most and least healthy places to live. In some parts of the United States, men and women are dying younger on average than their counterparts in nations such as Syria, Panama and Vietnam.

Overall the United States is falling further behind other industrialized nations, many of which have also made greater strides in cutting child mortality and reducing preventable deaths.

Medicynical note: We spend more per capita by a wide margin on health care but we forgot that preventing disease offers more benefits (at lower price) than treatment. Meanwhile we reap the consequences of smoking and obesity in our population.


Socioeconomic Status, Quality of Care, Outcomes in Lung, Pancreas and Esophageal Cancer

At ASCO 2011 there were very few studies on cost efficacy, it doesn’t seem to be an issue to researchers funded mainly by pharmaceutical manufacturers. There was however an interesting abstract (6004) which looks at the care provided and outcomes of patients in different socioeconomic groups.

The study was of patients with cancers of the lung, esophagus and pancreas which “account for over 35% of all cancer deaths in the US and a sizable share of cancer costs.”

The researchers from the University of Michigan used the SEER-Medicare data base and examined the effect of socio-economic status on treatment and 2 year survival rates. The authors found:

The lowest SES (socio-economic status) patients were more likely to require urgent or emergent admissions and to be treated at very low volume hospitals and non-teaching hospitals. For all three cancer types, low SES patients were more likely to receive no cancer-directed treatment (e.g., 60% of the lowest SES patients received no treatment for pancreas cancer). Receipt of cancer-directed surgery, chemotherapy, and/or radiation therapy was consistently higher for the highest SES patients, with most patients receiving at one type of treatment and many receiving a combination of treatments.

And concluded:

There is pronounced variation in types of cancer treatment received by different SES groups. Despite receiving more aggressive treatments, higher SES patients do not have improved survival rates.* Reducing variation in treatment strategies may improve healthcare efficiency without changing patient outcomes.

*emphasis by medicynic

Medicynical Note: I’m not sure what more there is to say. We have a primeval, possibly money driven urge, to do all modalities of treatment to patients with bad disease, especially to those with money, insurance or other resources. But we have no impact on the ultimate course of the disease.

This mania is costly. We are using drugs and procedures costing our health care non-system many thousands of dollars a month, uselessly. More careful shepherding of resources and more considered use of treatments would save money (lots) and not impact outcomes adversely.


Melanoma, Real advances

Malignant melanoma has resisted virtually all treatment approaches once it’s metastasized. It’s wonderful that there’s been progress at least for one subset of these patients. Abstract LBA4 ASCO 2011 also.

Early results in a study using the drug vermurafenib in melanoma patients with a specific tumor mutation (GRAF V600E) showed strong evidence of the drug’s efficacy. This mutation is found in 40-60% of patients with cutaneous melanoma. Whether this will result in prolonged remissions and significant life extension remains uncertain.

A previous phase 2 trial with this drug showed a rated of response of 57% with a duration of 6.7 months. A previously unheard of response rate in melanoma. This phase 3 trial compared the drug with dacarbazine alone which has response rates of 7-12% and an overall survival of 5-8 months.

This phase 3 trial found:

A total of 672 patients were evaluated for overall survival. The hazard ratio for death in the vemurafenib group was 0.37 (95% confidence interval [CI], 0.26 to 0.55; P<0.001)The survival benefit in the vemurafenib group was observed in each prespecified subgroup, according to age, sex, ECOG performance status, tumor stage, lactate dehydrogenase level, and geographic region (Figure 1B). At the time of the interim analysis, there were an inadequate number of patients in follow-up beyond 7 months in either study group to provide reliable Kaplan–Meier estimates of the survival curves.17 At 6 months, overall survival was 84% (95% CI, 78 to 89) in the vemurafenib group and 64% (95% CI, 56 to 73) in the dacarbazine group. Further follow-up is required.

Very hopeful, but very preliminary, results.

Medicynical notes: The discussion of the results in the NEJM article reported a relative reduction of 63% in the risk of death and 74% a tumor progression compared with dacarbazine. Dacarbazine is a poor comparator as it probably is not much better than placebo in this very resistant to treatment tumor.

I don’t argue that the new drug is not an advance but touting the improvements in outcome as a percentage rather than actual numbers overstates the benefit–not surprising that this is done in a drug company study.

You might want to look at the Kaplan-Meier survival curve in the article which shows the percent surviving (40%) in the two groups apparently merging at 9 months. The drug offers some benefit but it not a panacea.

Wonder what Roche will charge?


Health care: Our non system

This week’s at ASCO there were numberous examples of studies involving high priced drugs for treating cancer costing in the range of $60,000-$100,000 and more for the drug alone, most with very limited benefit. When one adds up other care required the yearly costs of following these patients approaches $150,000 or more. Consider that one year’s dialysis, all costs included, is in the range of $75,000. Where is the value in these new oncologic advances? True it’s wonderful that there is progress, but at what cost? Affordability? Reality?

Average individuals (median income in U.S. approximately $50,000) will can not pay more than their annual salaries for such limited benefits. Health insurance is a buffer but it doesn’t work if insurers won’t control costs. However, insurers have problems denying patients. The proposals to objectively (non-drug company sponsored evaluations) evaluate cost effectiveness would help with this. If a drug proved no better than standard and/or less expensive options there would be grounds for both the insurance company and physicians to use the more economic alternative. Patients, if they wished, could always opt to pay themselves for the more expensive choice.

Ryan, and his republican colleagues, find regulation to be abhorrent and one can predict that their “plan” will have few protections for those with serious illness and simply allow insurers to discriminate in their provision of coverage (charge unaffordable rates or not offer policies) rather than discriminate against expensive ineffective treatment alternatives.

Our population appears to have reservations about mandating that we all have insurance, high and low risk people. The mindset appears to be that ” I’m not sick, why buy insurance” and that “you can’t make me do anything.” But these same people have no aversion to appearing at ER’s and demanding free care (the most expensive, least efficient available); manipulating the system to get their parents into medicaid covered nursing homes; and demanding affordable health insurance at the moment they become ill.


Defying Gravity: Cancer Care Costs, Hepatoma, sorafenib

The American Society of Clinical Oncology meeting finishes and I’m left with a continued disbelief in treatments with limited efficacy costing in the range of $60,000-120,000/year. Patients are not cured; many studies report no survival benefit found as of yet (reports of delays of progression abound); and yet there appears little or no concern whether the advances are affordable by the various insurance schemes or individuals.

Consider the improvement provided by sorafenib compared with sunitinib in Hepatoma ( abstract 4000 at the meeting).

The report noted:

Median OS (overall survival) was 8.1/10.0 mo (HR 1.31 [95% CI: 1.13–1.52], P=0.0019); PFS was 3.6/2.9 mo (HR 1.12 [95% CI: 0.98–1.29], P=0.1386) and TTP (Time to Progression) was 4.1/4.0 mo (HR 1.13 [95% CI: 0.97–1.31], P=0.1785). OS for pts with hepatitis B (Hep B; Su 290/So 288; post hoc analysis) was 7.8/7.9 mo (HR 1.09 [95%CI: 0.9–1.32], P=0.236). In 526/541 pts evaluable for safety, all-causality, grade 3/4 adverse events (AEs) occurred in 82/73% of pts; the most common were thrombocytopenia (19%) and neutropenia (16%) for Su, and skin disorders (21%) for So. Discontinuations due to AEs occurred in 26/23% of pts. Serious AEs were noted in 44/36% of pts, with grade 5 AEs in 18/16%.

Neither drug seems particularly effective but the fact that there was any effect in this difficult cancer is considered an event.

Medicynical Note: Sofafinib costs in the range of $6000/month. It has a benefit of a few months over no treatment and perhaps 2 months over sunitinib, apparently in patients with associated Hep C. Cases of cancer associated with Hep B cases were equally “improved” OS 7.8 and 7.9 months.

It should be noted that when compared with placebo in an earlier study the results were similar, a 2-3 month improvement of overall survival.

Median overall survival was 10.7 months in the sorafenib group and 7.9 months in the placebo group (hazard ratio in the sorafenib group, 0.69; 95% confidence interval, 0.55 to 0.87; P < 0.001).


Tax Burden, Health Care: Europe vs the U.S.

Nice article in the NY Times by Bruce Bartlett on the policy choices, taxation and health care, comparing the U.S. and other OECD countries. He notes:

1. The U.S. has very low taxes by international standards:
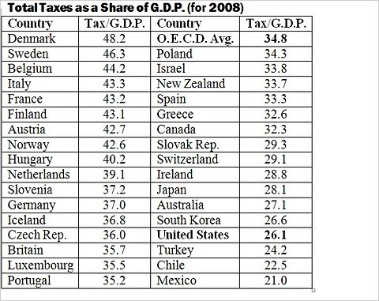


2. The difference in taxation is to a great degree the payment of health care costs in most industrialized countries by taxation and cash payments (family allowances) made to families in most Euopean countries.

He notes the impact of such payment on taxes:

The impact on the tax burden can be dramatic if one views family allowances as negative taxes. For example, in Luxembourg, an average married worker with two children pays a nominal income tax rate of 16.5 percent (including state and local income taxes), while an American in the same situation would pay 5.2 percent. But once family allowances are subtracted from the Luxembourg worker’s income-tax payment, the effective tax rate falls to just nine-tenths of 1 percent. (Medicynical note: lower than the U.S. )

3. Regarding health care in the U.S. national health insurance covers 72% of expenditures in other OECD countries and just 46.5 % in the U.S.

4. The U.S. pays more for health care than residents in any other major country. And the government share of current health spending that in the U.S. covers a just minority of citizens…

is about the same as total health care costs in many other countries, including (as a percentage of G.D.P.) Luxembourg (6.8 percent), Israel (7.8 percent), Japan (8.1 percent), Britain (8.4 percent) and Norway (8.5 percent).

That is, the proportion of GDP we spend now for just those on medicare, and medicaid in the U.S. non-system covers the total health costs in other countries. We are one of the least efficient, lowest value health care “systems” in the world. Exceptional!

Read the article, it’s short and clear.

Medicynical Note: The solution being offered by Ryan, provides less coverage for those in medicare and medicaid; does nothing about the 50 million uninsured. It will likely cut costs but also cut care provided and result in the deaths of our citizens. Amazingly modest proposal.


Drug Patents: Part of the Problem

Dean Baker in the Guardian, notes the obscenity of drug pricing and Senator Sanders’ solution.

We can do better – and Senator Bernie Sanders has proposed a way. He has introduced a bill to create a prize fund that would buy up patents, so that drugs could then be sold at a free market price. Sanders’s bill would appropriate 0.55% of GDP (about $80bn a year, with the economy’s current size) for buying up patents, which would then be placed in the public domain so that any manufacturer could use them at no cost.

Medicynical Note: Unlikely to happen but might put pressure on manufacturers to more reasonably price drugs.


Avastin; Ovarian Cancer 2.4 months Delay of Progression for $100,000

What’s missing from this week’s American Society of Clinical Oncology (ASCO) meeting is analysis of costs. Yesterday we noted exemestane prevented one cancer for 1.1 million dollars spent.

Today we have the story that Avastin is useful to extend the lives of ovarian cancer patients 2.4 months for an estimated $100,000 (cost of one year’s treatment with the drug) plus the expenses of other chemotherapy, doctors visits, and imaging studies–probably another $50,000. Abstract of study here.

The trial enrolled 1,528 women with newly diagnosed ovarian cancer, of whom 90% had advanced disease, Kristensen reported.

They were treated over an 18-week period with a standard chemotherapy regimen of carboplatin (Paraplatin) and paclitaxel (Taxol), with or without bevacizumab.

Patients who were treated with bevacizumab also had maintenance therapy with bevacizumab for another 36 weeks, while those in the other arm were simply observed.

The primary endpoint of the study, he said, is progression-free survival and on that measure, women in the bevacizumab arm had a 13% benefit, which was significant at P=0.039.

For those women, the median time to progression was 19.8 months, compared with 17.4 for those in the control arm, he said.

It was also noted in a quote from the author of the study Gunnar Kristensen that “Overall survival, he said, was less clear”

Medicynical Note: This was a drug company (Roche) sponsored study–Kristensen has a financial relationship with Roche. It’s probably too much to hope that the cost of the intervention would be mentioned, much less factored into the discussion of the results.


Exemestane Prevents Breast Cancer? Maybe. Costly? Definitely

This is the week of the American Society for Clinical Oncology’s meeting so we can expect to inundated with news of medical progress, some real, some maybe real, some imagined. But all can be expected to be costly.

One of the most publicized studies is that of using exemestane (Aromasin) to prevent breast cancer in women at moderately increased risk. 4560 women were randomly assigned to a group using the drug or to placebo. The abstract from an article on the study published this week in the NEJM states:

At a median follow-up of 35 months, 11 invasive breast cancers were detected in those given exemestane and in 32 of those given placebo, with a 65% relative reduction in the annual incidence of invasive breast cancer (0.19% vs. 0.55%; hazard ratio, 0.35; 95% confidence interval [CI], 0.18 to 0.70; P=0.002). The annual incidence of invasive plus noninvasive (ductal carcinoma in situ) breast cancers was 0.35% on exemestane and 0.77% on placebo (hazard ratio, 0.47; 95% CI, 0.27 to 0.79; P=0.004). Adverse events occurred in 88% of the exemestane group and 85% of the placebo group (P=0.003), with no significant differences between the two groups in terms of skeletal fractures, cardiovascular events, other cancers, or treatment-related deaths. Minimal quality-of-life differences were observed.

The drug has fewer side-effects than other agents used to prevent breast cancer (tamoxifen and the aromatase inhibitors) but still in 3-4% of patients severe joint pain was reported.

Medicynical Note: Exemestane (Aromasin) costs about $3600/year. In this study about 2280 (half of the number randomized) patients were treated with exemestane for three years and according to the study 21 fewer cancers occurred than in the placebo group. This reduction of incidence from 32 in placebo to 11 given drug was cited in news articles as a “65% reduction in cancer occurrence.”

The cost of this preventive strategy/case prevented is $3600 (yearly cost) X 3 (number of years treated) X 2280 (number of patients treated)/ 21 (number of cases of cancer prevented) and was $1,172,571/case prevented.

In fact, relatively few cancers occurred in either group (32 and 11). The reduction of 21 cases was significant but the cost/cancer prevented is prohibitive. Given that these patients will also be followed with mammograms and physician exams (adding to the cost) it’s doubtful that this intervention will lead to a measurable survival benefit.