What’s the real cost of Progress when a drug costs $100,000/year drug

It’s in vogue in medicine to market drugs offering slight benefit to desperately ill patients at cost of between $50,000 and $100,000/year.

What’s the real cost of these “advances.”

In a hypothetical (but typical) situation lets say the drug is used in 100 patients and compared with another group of 100 patients receiving placebo (or standard therapy).

As one would hope the group of patients receiving the study drug appears to have some response. In the distant past a response was defined as a decrease in tumor bulk of 50%. In recent years that definition has been broadened, some would say undermined, to mean that there was no evidence of tumor progression during treatment. Since we are in “modern” times lets use the definition of response being no progression.

We do our study and find in the group of patients receiving placebo (or standard therapy) 25% showed no progression. While in the study group receiving the new drug of 100 patients 40% showed no progression.

Drug companies take such data as evidence of the drug’s efficacy and try to get FDA approval. Note there is no evidence at this point of extension of life.

The real cost of this advance is interesting to contemplate. Consider treating 100 patients with a $100,000 drug–that’s 10 million dollars. Consider that just 40% get a “benefit” with the drug and 25% had the same “benefit” with placebo (or standard therapy)–and a marginal “benefit” at that. That means that 6 million dollars was spent on patient who got no “benefit” at all from the drug (the 60 of 100 patients without “benefit”). 2.5 million dollars on the 25 patients who would have shown no progression with placebo (or standard therapy). The incremental “benefit” of the drug over placebo or conventional therapy was therefore a total of 15 patients.

That means in our hypothetical but somewhat typical new drug situation 85 out of 100 patients will be treated with the $100,000/year drug and get nothing from it. 15 patients get a limited improvements. The cost/patient that improved is $100,000 X 100 patients treated/15 patients who get the improvement=$666,666 expended for each patient who improved. It should be noted that this is a cost per year figure for a single drug.

How much is a reasonable amount for the system to spend for an improvement. It’s been thought in the literature that between $50,000 and $150,000 per year of life gained was an affordable sum. It’s never been clear to me where these numbers came from but in the cost efficacy literature they seem to be the most used figures.

In our hypothetical situation our outcome was no progression of disease during the treatment period. But for the sake of our discussion lets say the study continues and the study patients (the 15% with benefit) lived a median of 2,3,4,5, or 6 months longer. For what it’s worth except for the very rare super effective new agent (Gleevec for example) most new biological agent’s improvement of survival is in the 2-6 month range.

If the median improvement is 2 months then the cost of a 12 month survival would be 6 X $666,666 (the cost/patient who benefitted) or about $4,000,000 to buy a total of a year’s survival time for patients who benefit from the treatment.

If the improvement is 6 months then the cost of 12 months survival would be 2 X $666,666 or in the range of 1.33 million dollars.

Neither would be considered cost effective by any of our current measures.

Medicynical Note: You won’t find the drug companies funding cost efficacy studies nor touting their results as cost efficient. Instead our hypothetical study would be touted as showing a 60% improvement in response rates between placebo and study group. (40% response rate with drug/25% with placebo or conventional Rx X 100=160%) It won’t be easy to find out that the difference between a “response” to placebo and the study drug was 15% (40% vs 25%) or that the benefit was just 2-6 months, if that. That the American way of drug marketing.

In case you think the above is exaggerated consider these from real life NEJM 355:2542-2550

The median survival was 12.3 months in the group assigned to chemotherapy plus bevacizumab, as compared with 10.3 months in the chemotherapy-alone group (hazard ratio for death, 0.79; P=0.003). The median progression-free survival in the two groups was 6.2 and 4.5 months, respectively (hazard ratio for disease progression, 0.66; P<0.001), with corresponding response rates of 35% and 15% (P<0.001). Rates of clinically significant bleeding were 4.4% and 0.7%, respectively (P<0.001). There were 15 treatment-related deaths in the chemotherapy-plus-bevacizumab group, including 5 from pulmonary hemorrhage.

Or this from today’s (April 25, 2010) Seattle Times:

Dendreon’s case rests largely on a study of more than 500 men with an advanced form of prostate cancer that spread to other parts of their bodies. Of the men who got Provenge, nearly a third were still alive in three years, compared with less than a quarter of those who got placebos. (medicynical emphasis) The vaccine boosted median survival time by 4 months, from 22 months in the placebo group to 26 months in the Provenge group.

How much difference is there between nearly a third and less than a quarter? I wonder who provided this verbiage? I figure an 8% benefit. Affordable?


Another Marginal $100,000 treatment–Provenge

Provenge, why so expensive? Yes there are development costs and clincal trials to pay for but not enough, in my view, to justify the pricing. We talk about holding practitioner’s fees down by looking at outcomes, shouldn’t we do the same with drugs that cost 100 times more?

The FDA by the way is not allowed to assess cost efficacy, their mandate is to document lack of harm and have evidence of minimal benefit. Interestingly, many times in the past the initial studies benefit was proven to be overstated and the risks understated.

The treatment’s benefits are modest. But as the first product of its type to emerge from decades of often-frustrating research, Provenge could help open doors for immune-based therapies against a range of cancer.

Analysts estimate a course of Provenge will cost between $50,000 and $75,000. As many as 100,000 men a year develop the advanced form of prostate cancer the treatment would initially be prescribed for. At that rate, Dendreon could rack up well over $1 billion in annual sales in a few years, said David Miller, president of Biotech Stock Research in Seattle. If the company isn’t swallowed up by a pharmaceutical firm — a big “if” — its success would boost the region’s stature and draw as a biotech hub.

The vaccine boosted median survival time by 4 months, from 22 months in the placebo group to 26 months in the Provenge group.

Medicynical note: The company claims an investment of $750,000,000–it’s been thought by many that these “investments” are routinely overstated (Read Marcia Angell and her book The Truth About the Drug Companies: How they Deceive Us and What to Do about it). Dendreon’s estimate is that the drug in the first year will provide over a billion dollars in sales. Don’t expect the prices to go down with time.

It is the American way to reward innovation and this approach clearly is innovative, though modestly effective. But can any system afford such pricing for an incremental (3-4 month), if that, improvement? Isn’t there a more efficient way to drug development? If health insurance wasn’t there to buffer patients and their families could the majority of us afford such an “advance.” Can we as a failing society, slowly bankrupting ourselves, afford it?


Polio Resurgent-A warning for vaccine deniers

Despite a worldwide vaccine program, polio is showing signs of resurgence. The problems? Incomplete vaccine use and availability–partially driven by misinformation and rumor mongering– lack of information, and a poor distribution system.

Polio was spreading across Africa, even after he gave $700 million to try to wipe out the disease.

That outbreak raged last summer, and this week a new outbreak hit Tajikistan, which hadn’t seen polio for 19 years.

“There’s no way to sugarcoat the last 12 months,” Bruce Aylward, a WHO official, told Mr. Gates in the meeting in the underground pandemic center last June. He described how the virus was rippling through countries believed to have stopped the disease.

Part of the problem is misinformation:

Men like the sultan are important allies. In 2003, Islamic leaders in northern Nigeria spread rumors that polio vaccines sterilized Muslim girls. Leaders halted vaccinations, allowing the virus to spread. The WHO said the virus eventually infected 20 countries.

Medicynical Note: For more information, you should read the full article.

This should be a warning to those in our country who deny the benefits of vaccines and refuse to allow their kids this protection. It seems redundant to remind people of the seriousness of this disease which causes permanent neurological disability, for which there is no cure.

The article also approaches the dilemma of whether to target single diseases (following the model of the successful smallpox vaccination program of the 60’s) or include vaccination in a broader based approach to health and hygiene. From a medicynical point of view, I would point out that one of these goals might be achievable in our lifetimes, the other not.


Health Insurers (Wellpoint) — It’s not about health care, its about the money

Get a disease and really need your health coverage, then Wellpoint should NOT be your insurer!

Shortly after they were diagnosed with breast cancer, each of the women learned that her health insurance had been canceled. There was Yenny Hsu, who lived and worked in Los Angeles. And there was Patricia Reilling, a successful art gallery owner and interior designer from Louisville, Kentucky.

They had no idea that WellPoint was using a computer algorithm that automatically targeted them and every other policyholder recently diagnosed with breast cancer. The software triggered an immediate fraud investigation, as the company searched for some pretext to drop their policies, according to government regulators and investigators.

Medicynical Note: It’s so outrageously hypocritical that it makes a medical cynic cry (with joy). Imagine all the blog posts that will arise from these bizarre but real policies.


Berwick’s Triple Aim–Costs matter, duh!

Dr. Don Berwick has been named Medicare and Medicaid administrator. His views on “The Triple Aim“: Care, Health and Cost” provide a blueprint for change. Whether we are able to adopt some of these aims is a big question”

If we could ever find the political nerve, we strongly suspect that financing and competitive dynamics such as the following, purveyed by governments and payers, would accelerate interest in the Triple Aim and progress toward it:
(1) global budget caps on total health care spending for designated populations
(2) measurement of and fixed accountability for the health status and health needs of designated populations,
(3) improved standardized measures of care and per capita costs across sites and through time that are transparent,
(4) changes in payment such that the financial gains from reduction of per capita costs are shared among those who pay for care and those who can and should invest in further improvements, and
(5) changes in professional education accreditation to ensure that clinicians are capable of changing and improving their processes of care.

Medicynical Note: I like the idea of global budgets. We need to change the money driven attitudes of our non-system and balance it with reality, quality and the notion of performing a service.

People always have the option of funding, themselves, that which is not able to be covered or which is deemed not good enough for coverage by the general program.


Erlotinib (Tarceva) Maintenance in lung cancer–or why health care is so expensive

Non-resectable metastatic non small cell lung cancer is a uniformly fatal illness. Patients may respond temporarily to treatment but in virtually all cases the disease will eventually progress. Therapy, depending on the extent of disease, is a combination of chemotherapy and radiation.

Erlotinib (Tarceva), a epidermal growth receptor inhibitor (HER1/EGFR), was recently approved by the FDA as maintenance therapy for the disease in patients with stable disease after treatment with platinum based therapy. The approval was based on the results of the Saturn study which was reported at the 2009 ASCO meeting.

The study showed:

Response rate was 12% with E versus 5% with P (platinum based treatment). Disease control rate (complete response + partial response + stable disease >12 wks) was
40.8% with E versus 27.4% with P (p<.0001). OS (Overall survival) data are not yet
mature.

Further analysis released in August 2009 showed:

The study showed that patients with NSCLC treated with Tarceva had a 23 percent improvement in overall survival compared with patients who received placebo (hazard ratio=0.81; p-value=0.0088). The hazard ratio, which assesses risk in the overall trial population, is widely recognized as the best measure of overall benefit in large randomized clinical trials. A hazard ratio of less than one for survival indicates a reduced risk of death. The median survival (a single point estimate of benefit) for patients receiving Tarceva was 12 months versus a median survival of 11 months for patients receiving placebo. (medicynical emphasis)

Medicynical note: The yearly cost of Tarceva is in the range of $30,000-60,000/year. This according to the Saturn study buys an improvement in median survival of 1 month. Added to this are the cost of the initial platinum based chemotherapy, radiation if given, doctor’s fees and imaging costs.

Is it cost effective to spend over $30,000-60,000 or more depending on length of treatment for a median survival improvement of 1 month? If not covered by insurance would you pay for this drug? Would you expect someone else to pay for it for you?


Pharmaceuticals Profitability makes Walmart feel Sick

Compare the revenues and profits of these companies : (Data from Fortune 500 2010)


Medicynical Note: Using profits as a percent of total revenue the pharmaceutical industry may well be the most profitable sector in the Fortune 500. For example, Walmart offers a paltry 3.51% of revenue as profit, Exxon 6.77%, Apple a mere 15.6%. Drug companies and these are not the foreign based big earners garner Johnson and Johnson 19.8%, Pfizer 17.6%, Merck 47.2% and Abbott 19.1%, Lilly 19.8%, Bristol-Meyer Squibb 49.05%.

You gotta feel sorry for the poor drug companies. Guess who pays?


Glioblastoma–We Need Better Treatments, but can we afford them?

Our non-system of care’s great virtue, we’re told, is that the profit motive encourages development of new approaches. The problem is that the profit and costs in our cost plus system of reimbursement are so great that the system and individuals can’t afford the new “advances”–which by the way are mostly of marginal benefit.

For the past thirty years in oncology we’ve been combining therapies to improve outcomes. When each of the drugs in combination cost under $1000/month, such combinations were doable. While expensive for the time, their cost does not compare with the current situation of drugs costing $10,000/month and more.

One example of what’s happening is in the treatment of glioblastom multiforme, the most malignant tumor of the brain, the disease from which Teddy Kennedy succumbed. Standard treatment used to be radiation with or without chemotherapy. Until recently the chemo was older agents that were moderately priced. With the advent of Temodar a few years ago costs have spiraled.

He will need to take 140 mg of temozolomide (75 mg/m2 per day) for 42 consecutive days. Each 140-mg capsule of temozolomide costs $283.32 ($1416.59 for 5 capsules) and the total for 42 capsules is $11,899.44. For the first cycle of metronomic temozolomide (5 days at 150 mg/m2 per day), the patient will need to take 2 of the 140-mg capsules daily for a total cost of $2833.20. For subsequent cycles of metronomic temozolomide (200 mg/m2 per day), the patient will need to take one 250-mg capsule, one 100-mg capsule, and one 20-mg capsule each day for 5 days. The prices for 5 each of the 250-mg, 100-mg, and 20-mg capsules, respectively, are $2334.29, $933.70, and $186.71. The total cost for each 5-day cycle of metronomic temozolomide at 200 mg/m2per day is therefore $3454.70.

If the same patient experiences GBM recurrence, his chemotherapy may be changed to bevacizumab and irinotecan. He will need 10 mg/kg of bevacizumab every 2 weeks. At 155 pounds, he is roughly 70 kg, so he will need 700 mg of bevacizumab. The cost of bevacizumab is $687.50 per 100 mg, so the cost of each infusion will be $4812.50.

Medicynical Note: Remember, each of these costs is for the drug alone. Additional expenses include physician’s fees, imaging costs (MRI’s, etc), other medications and nursing support.

Temozolomide has limited benefits:

Median survival in the radiation-plus-temozolomide group was 14.6 months, compared with 12.1 months in the radiation-only group. After two years, 26.5 percent of patients in the radiation-plus-temozolomide group were alive, compared with 10.4 percent of those who received radiation only. After 5 years, 9.8 percent of patients in the radiation-plus-temozolomide group and 1.9 percent of those in the radiation-only group were still alive.

And in Lancet 2009:

278 (97%) of 286 patients in the radiotherapy alone group and 254 (89%) of 287 (Medicynical note: patients who died over 5 years)

Regarding bevacizumab in glioblastoma, its use is based on small non randomized studies:

One of the trials (known as AVF3708g, or BRAIN) involved 167 patients with glioblastoma who had progressed on radiation and temozolomide (Temodar, Schering) and who then received bevacizumab either alone or in combination with irinotecan. According to an FDA analysis of the study, tumor responses were observed in 22 of 85 patients (26%) treated with bevacizumab alone, and the median duration of response was 4.2 months. (note: that’s a response in just 22 patients. The others were treated, 63 patients and had no benefit whatever)

In another trial (NCI 06-C-0064E), 56 patients with recurrent glioblastoma were treated with bevacizumab alone. Responses were observed in 11 patients (20%), and the median duration of response was 3.9 months. (Note: that’s a response of 3.9 months in the 11 patients who responded. None of the 45 other patients benefited)

There are no data so far from randomized trials for overall survival.

Medicynical Note: The question is can any system afford drugs costing tens of thousands of dollars/month? Can it afford such drugs in non curative situations? Can it afford using two such drugs simultaneously or in sequence if they provide temporary benefit for just a few of the patients treated?

Should we revisit how we develop new drugs? Revise patent law to encourage efficiency and affordability? Factor in cost efficiency when approving drugs? Consider whether our current system of granting generation long monopolies on new drugs is in the best interest of patients? Or the system?

It’s amazing but we have developed a system of drug development that is unaffordable, inefficient, and doomed.


The Tyranny of Expectations–Health Care and it’s Reform

We pay more for care than anywhere else in the world.


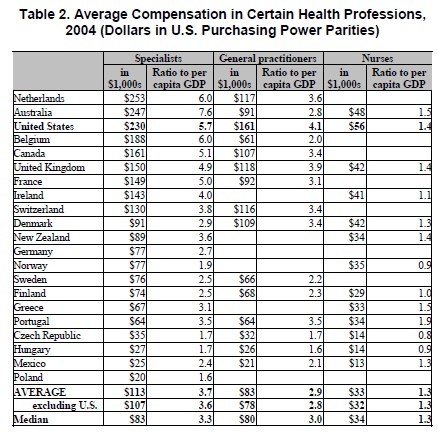
Our doctors are among the highest paid in the world


Source: Congressional Research Service (CRS) analysis of Remuneration of Health Professions, OECD Health Data 2006 (October 2006), available at [http://www.ecosante.fr/OCDEENG/70.html].

Our medical care, administrative, drugs and medical technology costs are also the highest in the world. This from economix:

One thing Americans do buy with this extra spending is an administrative overhead load that is huge by international standards. The McKinsey Global Institute estimated that excess spending on “health administration and insurance” accounted for as much as 21 percent of the estimated total excess spending ($477 billion in 2003). Brought forward, that 21 percent of excess spending on administration would amount to about $120 billion in 2006 and about $150 billion in 2008. It would have been more than enough to finance universal health insurance this year.

The study used a measure of administrative costs that includes not only the insurer’s costs, but also the costs borne by employers, health-care providers and governments – but not the value of the time patients spent claiming reimbursement. These authors estimated that in 1999, Americans spent $1,059 per capita on administration compared with only $307 in purchasing power parity dollars (PPP $) spent in Canada.

These expenses have to do with expectations:

  • Patients expect care: Price should not be an issue, at least to them. These expenses have been buffered by private insurance, government programs, and to a lesser degree our altruism (mandatory access to ER care in emergencies).
  • Health care providers also have expectations: They went to great expense and time to go through training and many have huge debts to repay. Their expectation is that they earn an excellent living.
  • Medical Insurers expect that they will keep 20% of premiums for their services–contributing to the highest administrative expenses in the world–and million dollar salaries and benefits for their executives
  • Medical suppliers, pharmaceutical companies: Huge international corporations also have high profit expectations. Patent laws provide exclusivity for a generation. Drugs are priced not by their cost of development or manufacture but whatever the market will bear. So those with serious illness pay more–because they have to.
  • Cost Efficiency is an oxymoron in our non-system: When you have a life-threatening illness cost, efficiency and “shopping” for the best deal are not priorities. Unfortunately, efficacy gets lost in the mix and patients and their insurers, (honoring the patient’s desires) pay exorbitant premiums for treatments that often offer very limited benefit.

Medicynical Note: Expectations and money:

It would seem a given in this the wealthiest (I think that still is the case) economy in the world that health care should be accessible and affordable to all. That is certainly the case in other industrialized nations.

Industry has figured out that health care is not cost sensitive. Why be efficient when the system will pay whatever is demanded. Patients are in a bind and buffered by third party payers; doctors earn more by doing more; industry charges cost plus at every level. Our health care system has become the moral equivalent of the Air Force’s $600 toilet multiplied 100 fold. We now spend more for a single drug than the average and median income–amazing.

One would think that with all this spending everyone would have some coverage, but it’s a fact that we have 50 million uninsured and still spend more per capita by a wide margin than anywhere else in the world.


Why I NEVER Watch Fox News