Oregon’s New Direction? Is it New, Will It Work?

After hearing platitudes from politicians–we’re the best…….etc…–it’s refreshing to find one who seems to understand the problem.

Most of that legislation — and most of the health care debate in America for the last 50 years — has been how to pay for health care. I don’t think the problem is how you pay for health care. It’s what we’re buying. We’re buying a product that is very ineffective, very inefficient, and doesn’t have real impact on population health.
Our population health statistics in this country are a little bit better than Cuba’s, and we spend huge sums of money. So, ultimately, we have to change the way health care is organized and delivered, and we need to recognize that the objective of the health care system is not simply to finance medical care. It’s to keep people healthy.
And:
You can cut people from Medicaid, but where do they go? They go to the emergency room, and so then you’re paying for a stroke rather than managing their blood pressure. They don’t go away.
The only way that saves you money … is if you also pass a law that says, ‘If you show up at the ER without insurance coverage, we’ll let you die on the ambulance ramp.’ That’s the only way, and no one is suggesting that.
Medicynical Note:  Health care has long been a unbalanced equation.  On one side we have unlimited expectations of care paid for by insurance or just some one else; expectations of unlimited profits by providers (hospitals, pharmaceutical companies, doctors); and a paradoxic lack of concern about costs.  On the other hand we have no viable funding scheme to meet these expectations.

Health care inflation is like a bubble fed by our willingness to use debt both personal and national to pay anything  demanded for even a  limited benefit –a little like buying tulips in 17th century Holland.   I won’t repeat the litany of our tolerance of inefficiency and the wide difference in  costs between our non-system and more systematic approaches of every other industrial nation.  We are  unique (American exceptionalism strikes again) and  on an unsustainable course.

Our republican friends want  an as yet undefined free market system.  What they mean is anyone’s guess.  One could envision that under such a system insurers (provider) would be “free” to   limit their risk and deny coverage (service) to anyone they chose–as any business does.   Hospitals would be “free” to deny service to those unable to pay for service.

Where this “free market”  leads is anyone’s guess. If  we are willing to deny access to care to people who can’t pay (you might reread Jonathan Swift’s A Modest Proposal) in our “free market,”  it will be a public health disaster.

If we as a nation feel some responsibility to assure  access to care we’ll have a system with  multiple levels of care quality and service, essentially one of explicit economic rationing.     It  would, at a minimum, require a  complicated formula for government subsidization of those unable to afford insurance.

In the end we’ll get what we deserve.

25% Overuse of Implantable Cardioverter (ICD)

As noted in JAMA, implantable cardioverters are being overused. 25% of patients in the study cited did not have the accepted indications for this expensive procedure. Furthermore:

Patients who received a non–evidence-based ICD compared with those who received an evidence-based ICD had a significantly higher risk of in-hospital death (0.57% [95% confidence interval {CI}, 0.48%-0.66%] vs 0.18% [95% CI, 0.15%-0.20%]; P <.001) and any postprocedure complication (3.23% [95% CI, 3.01%-3.45%] vs 2.41% [95% CI, 2.31%-2.51%]; P <.001).

Medicynical Note: We think of the art of medicine as making treatment decisions using science as well as instincts based on the provider’s unique knowledge of the patient, local standards and what is medically indicated.

In the JAMA study 25% of patients received ICD’s did not have the established indications for the procedure and as a group these patients had worse outcomes. Presumably their doctors felt the use of the ICD indicated (applying the “art of medicine”). As costs have increased (an ICD procedure is $50,000 or more) and better tracking of outcomes reveal that overuse leads to more complications and worse outcomes, I’m not sure we can afford this type artistry.


The Game of Health Care — Another Great Moment in Medicine

I can recall a MAD Magazine illustration series (drawn by Kelly Freas) called “Great Moments in Medicine.” It was a parody of one of the “ethical” pharmaceutical company’s ad campaigns. Except in the MAD magazine case the great moment was presenting the bill.


In today’s Times there is another great moment.   Drug companies distributing coupons to decrease co-pays on their expensive drugs so as  to increase their  use rather than equally effective less expensive generics. With the coupon the patient’s out of pocket expense was the same. but for  insurers the cost was many times more. Guess who pays for this with increased insurance premiums?

Drug companies say the plans help some patients afford medicines that they otherwise could not.

But health insurers and some consumer groups say that in many cases, the coupons are just marketing gimmicks that are leading to an overall increase in health care costs. That is because they circumvent the system of higher co-pays on costlier drugs that insurers use to encourage consumers to use less expensive products.

One example was a one a day patented formulation of the generic drug minocycline:

A month’s supply of Solodyn sells for more than $700 on drugstore.com, compared with about $40 a month for capsules of generic minocycline, which are generally taken twice a day.

Almost 20 times the cost.

Medicynical Note: Is it any wonder that our non-system of health care is bankrupting us?

Suppliers (and insurers at times) game the system to maximize profits. Patient care? Cost efficiency? Not our department.


Are We Insane? America from a European Perspective

A U.S. citizen living abroad on Alternet comments on an article in  Der Spiegel “A Superpower in Decline”:

The European Union has a larger economy and more people than America does. Though it spends less — right around 9 percent of GNP on medical, whereas we in the U.S. spend close to between 15 to 16 percent of GNP on medical — the EU pretty much insures 100 percent of its population.

The U.S. has 59 million people medically uninsured; 132 million without dental insurance; 60 million without paid sick leave; 40 million on food stamps. Everybody in the European Union has cradle-to-grave access to universal medical and a dental plan by law. The law also requires paid sick leave; paid annual leave; paid maternity leave. When you realize all of that, it becomes easy to understand why many Europeans think America has gone insane.

The article in Der Speigel is a broad review of the history of our economic/political problems, (including such diverse issues as Florida, tea parties; Glenn Beck), xenophobia, and what Europeans perceive as  the slowly failing American society.

Medicynical Note:  I don’t see solutions in the short-term.  We have one party trying it’s best to have the other fail and the second party will of course do no less if they should lose power.  Somewhere our non-system of politics has failed us.  The future?  It’s very hard to be optimistic.  Maybe a divided government will work………

Spinal Fusion Surgery — Big benefit to doctors, limited benefit to patients

Bloomberg has an interesting article on the limited medical benefit of spinal fusion to patients–but big financial benefits to doctors, medical practices and suppliers (Medtronic). The article documents at least the appearance of, if not actual, conflicts of interest; high costs $135,000 for the surgery (yes on one patient); $800,000/year incomes for the orthopedists–three times that of pediatricians.

The possibility that many of these and other surgeries are needless has gotten little attention in the debate over U.S. health care costs, which rose 6 percent last year to $2.47 trillion. Unnecessary surgeries cost at least $150 billion a year, according to John Birkmeyer, director of the Center for Healthcare Outcomes & Policy at the University of Michigan.

“It’s amazing how much evidence there is that fusions don’t work, yet surgeons do them anyway,” said Sohail Mirza, a spine surgeon who chairs the Department of Orthopaedics at Dartmouth Medical School in Hanover, New Hampshire. “The only one who isn’t benefitting from the equation is the patient.”

There’s lots to this article including evidence that fusion is no better than physical therapy for disc related pain in several studies–only a 47% success rate for surgery in one U.S. study;  high complication rates for surgery;  direct payments from the medical supplier (Medtronic) in the form of royalties and consulting fees to doctors (as high as $440,000/year to an individual doctor and 1.75 million to a practice in Minneapolis).

Medicynical note: Not a pretty picture of American medicine. Costly, open conflicts of interest, use of aggressive expensive unproven procedures over more conservative approaches–with the same or worse outcomes.  Is it any wonder that our costs are one and half to two times that of other industrialized countries.

The “free market” encourages entrepreneurs to find ways to take advantage of markets, sometimes that leads to better outcomes and more efficiency but in medicine it seems to encourage waste, high cost and over-utilization.

Doctor’s fees, Medicare and Value

Two interesting reads on controlling costs and maintaining quality of care.

Ewe Reinhardt discusses the problems with our current reimbursement system and his thoughts on changes:

Medicare raised physician fees only 7 percent (an average of 0.75 percent a year), while the Medicare Economic Index (or M.E.I.), which tracks costs incurred by medical practices, rose 34 percent (an average of 3.3 percent annually).

Even so, Medicare’s spending on physician services per beneficiary rose 61 percent, an average annual compound rate of 5.4 percent a year.

The bulk of this increase in medicare spending therefore was on procedures, both diagnostic and therapeutic rather than the evaluation and management. This explains the  low rate of increase in the incomes of primary care people–the ones most of us rely on for management or our problems. Correcting the imbalance in incomes between these doctors and proceduralists is the challenge for the future and is discussed by Reinhardt.

The traditional working assumption had been that, in treating their patients, physicians are impervious to such financial incentives. Many, most likely, are. But a growing body of research has chipped away at the general validity of that assumption – hence the growing disillusionment with the hallowed fee-for-service method of compensating physicians.

He also discusses the Rivlin-Ryan plan for medicare reform:

Under the Rivlin-Ryan plan, the problem of paying the providers of health care would no longer be visible and for government to solve. Instead, it would be the product of private and presumably secret deals between private health plans and the providers – and, indirectly, the elderly, who would be made to bear the risk of rising payments to providers.

Another approach is taken in an article in the New England Journal of Medicine, “What is Value in Health Care” and “Measuring Healthcare Outcomes.”

Achieving high value for patients must become the overarching goal of health care delivery, with value defined as the health outcomes achieved per dollar spent. This goal is what matters for patients and unites the interests of all actors in the system. If value improves, patients, payers, providers, and suppliers can all benefit while the economic sustainability of the health care system increases.

Value — neither an abstract ideal nor a code word for cost reduction — should define the framework for performance improvement in health care. Rigorous, disciplined measurement and improvement of value is the best way to drive system progress. Yet value in health care remains largely unmeasured and misunderstood.

Read the article for the author’s suggestion for incorporating value into the patient care question.

Medicynical Note: Unless we  find a way to incorporate value (bang for the buck) in medicine we’ll spend ever increasing amounts on health care; have more people uninsured as they can’t afford care; and continue on the path to explicit financial rationing of health care–and system failure.

The Future of Health Care — Reality Bites

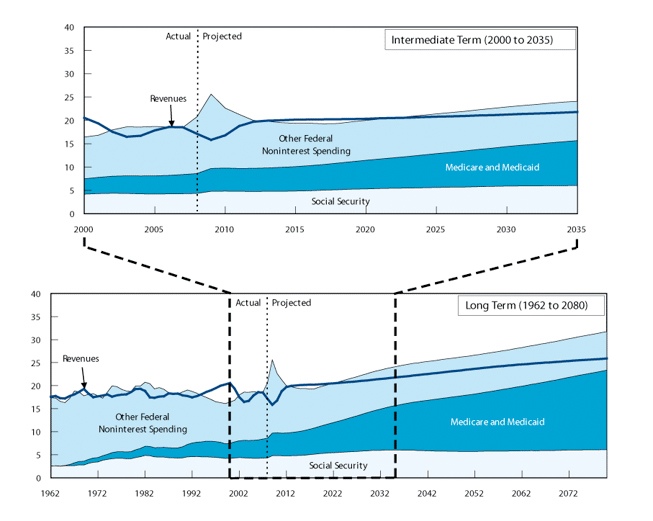
The following is from the CBO’s analysis of our economic future. (June 2009)

Holding down the spiraling levels of debt projected under either scenario could therefore result in significant economic benefits. However, accomplishing that goal would require some combination of substantial revenue increases and substantial spending decreases relative to current law. Those changes would have their own economic and social costs.

One policy that would prevent the increase in debt would be to raise revenues in line with the projected rise in spending. As evidenced by the estimated fiscal gap, the required increase in revenues under that approach would be large. If the increase occurred through higher marginal tax rates, incentives to work and save would be reduced and economic growth would slow.

An alternative policy would be to hold the growth of spending in line with the growth of the economy. That approach would require significant changes in the Medicare and Medicaid programs. Many experts believe that a substantial share of spending on health care contributes little, if anything, to the overall health of the nation, so changes in government policy have the potential to yield large reductions in federal spending without harming health. However, translating that potential into reality would require tough choices. It would ultimately depend on policymakers’ willingness to put ongoing pressure on the health sector to achieve efficiencies in the delivery of health care.

Reducing other federal spending significantly below the baseline levels would be difficult as well. Spending on Social Security has risen from almost 4 percent of GDP in the 1970s to almost 5 percent today and will increase to 6 percent in 2035 as the baby boomers retire. Other non-health, non-interest spending averaged almost 14 percent of GDP in the 1970s but has shrunk to about 10 percent of GDP over the past 15 years—aside from the current burst of spending in response to the recession and the financial crisis. Such spending is projected to decline further over time in CBO’s 10-year baseline.


Fine discussion by Brad de Long, (inflation economics lecture) of economic history, current high deficits and the decisions we face in meeting our economic commitments– and sustaining our health care non-system. The decisions and alternatives are enlightening.

He asks what we should do about it?

What do people think is the most likely outcome from this situation?
1. Come 2060 will we have raised taxes by a lot? We could double income taxes between now and 2060 and barely pay for extra government health spending.
2. Will we have cut doctors’ wages and enslaved them by drafting them into a socialist national health service?
3. Will we have abandoned our egalitarian healthcare beliefs?
4. Will the healthcare efficiency cost-effectiveness fairy have come and rescued us?
5. Or will the federal government as we know it will have collapsed and those of us who are still alive be involuntarily starring in a remake of Mad Max: Beyond Thunderdome?

Medicynical Note: Our non-system is not designed to deliver optimal care to our population but rather to provide excess profits to providers, suppliers and insurers. Over the years oversight, fiscal responsibility, efficiency and value have been degraded to the point of nonexistence. We therefore spend twice as much as most other places in the world; have reasonably good outcomes for those with access to care but mediocre population statistics (overall length of life, childhood statistics, prevention of preventable diseases, etc) presumably influenced by the 50 million people without insurance and those with limited access through such programs as Medicaid. We’re paying more but getting less benefit, this in the country that once fancied itself as the most productive and presumably efficient in the world.

We can continue to delude ourselves that we are the best in the world (as some radio hosts and 1/2 term governors do) or face reality that we are on an unsustainable path and do something.


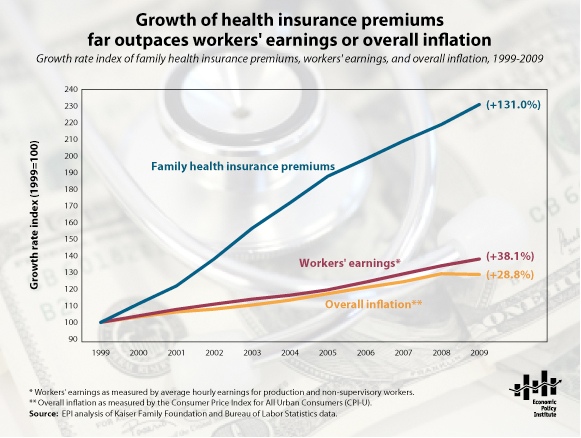
Health Care Costs vs Earnings

Wondering where our money for discretionary expenditures went?


What’s more:( From Sept 2010)

This morning’s release by the U.S. Census Bureau of the 2009 poverty and income data was yet another reminder of the severity of the Great Recession that began in December 2007. The data show that the poverty rate increased from 13.2% in 2008 to 14.3% in 2009, the highest rate since 1994. Furthermore, for the first time on record, the nominal (non-inflation adjusted) income of the median, or typical, household actually fell, from $50,303 in 2008 to $49,777 in 2009. Inflation was negative from 2008 to 2009, dropping by 0.4%, so real (inflation-adjusted) income did slightly better, dropping $335, or -0.7%, from $50,112 in 2008 to $49,777 in 2009.

Medicynical Note: Those expecting consumer spending to bail out the economy are kidding themselves.


Hospital Saves Mother, Loses Catholic Hospital Status

When churches do religion they apparently do it well. When they choose to practice medicine they bungle, despite their “infallibility.”

In this situation the hospital, after doing an appropriate ethical review, saved the life of a woman having life threatening complications from a pregnancy– hypertension, probably eclampsia.

The church’s reaction to this life saving act:

The Roman Catholic Diocese of Phoenix stripped a major hospital of its affiliation with the church Tuesday because of a surgery that ended a woman’s pregnancy to save her life.  

The woman is in her 20s had a history of abnormally high blood pressure when she learned of her pregnancy. After she was admitted to the hospital with worsening symptoms, doctors determined her risk of death was nearly 100 percent.

Medicynical note: If a loved one were pregnant, I would not advise using a hospital blindly adhering to the catholic church’s wishes. Medieval notions in the modern era unfortunately lead to remarkable distortions which in this case threatened life.

Market Manipulation (Compath)

Campath, a drug used for chronic lymphatic leukemia, has been found to have some activity in multiple sclerosis. The manufacturer, Genzyme Corp., is under pressure of a hostile buyout and is in discussions with Sanofi regarding the liklihood of future profits for this drug, as noted here. In the article the difference in pricing for Campath as a leukemia drug and as a potential MS treatment was noted:

Most MS drugs, such as Biogen Idec Inc’s (BIIB.O) Tysabri, cost more than $40,000 a year. A new oral drug made by Novartis AG (NOVN.VX) called Gilenya costs roughly $50,000 a year.

Campath sells for a fraction of that. As a result, Genzyme has to persuade governments and insurance companies to pay a higher price for the drug as a treatment for multiple sclerosis than it does as a treatment for cancer.

Genzyme says it is confident it can find a way to do it — possibly by withdrawing the drug from the market as a cancer treatment and providing it for nothing.*

Medicynical Note: Drugs costing tens of thousands of dollars per year trade on the desperation of patients with serious illness and are part of reason our health care expenses are soaring. (17% of GDP) From the above it’s clear that Compath was profitable at the lower price charged chronic leukemia patients. Seeing an opportunity to charge more for a larger patient population the company of course does what any for for profit enterprise would do, gouge their customers.

Shouldn’t health care be different? Can such market manipulation be legal, after all these drugs are protected by a government provided monopoly (patents)? Or perhaps should this type government intervention in “free” markets (patent protection) be done away with?

*Addendum: I note on December 22 that the above discussion of pricing has been removed from the Reuters article. Why? Too embarrassing?

However, the quote can be found on the CNBC site here. (and also on other sites by googling the text)